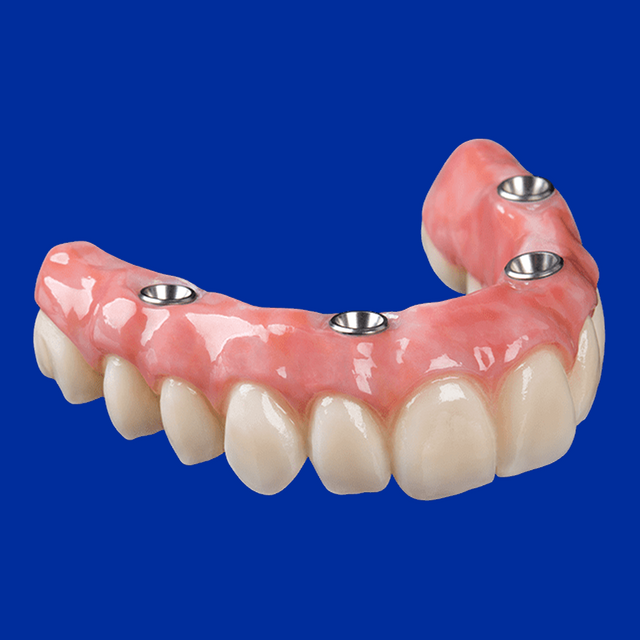
Choose a screw-retained implant crown whenever the screw access, straight or angled, exits occlusally or through the cingulum: it is retrievable and puts no cement in the mouth. Choose a cement-retained implant crown when access would exit facially beyond an angled channel's range, when an intact occlusal surface matters, or for short spans with margins at or above the mucosa. Both survive about equally well; the complications differ.
The difference shows up after delivery: whether a loose screw or a chipped cusp is a quick chairside fix, and whether cement is hiding below the mucosa, where it is hard to see and harder still to spot on a radiograph. Here is what the reviews, trials and ITI consensus show, turned into a decision guide and an Rx checklist.
What Is a Screw-Retained Implant Crown?
A screw-retained implant crown is fastened to the implant, or to a multi-unit abutment, by a screw through an access hole in the crown; the hole is then sealed. The screw holds it, so it comes off by opening the hole and unscrewing it. Chairside, that makes a loose screw or a chipped cusp a quick fix. The catch: the hole must exit lingually or occlusally.
What Is a Cement-Retained Implant Crown?
A cement-retained implant crown is cemented onto an abutment that is screwed into the implant, and the crown has no access hole. Cement holds it, so it does not simply unscrew: getting it off is harder. Chairside, that means an intact occlusal surface and no hole to hide, but excess cement must come out, and full removal below the mucosa is hard to guarantee.

The Trade-Offs at a Glance
What differs is what goes wrong, and how easily it is fixed:
| Criterion | Screw-retained | Cement-retained |
|---|---|---|
| Five-year survival | 95.55% | 96.03% (no significant difference) |
| Retrievability | Unscrew and remove | Harder: the abutment screw sits under a crown with no access hole |
| Cement near the tissue | None in the mouth; any Ti-base joint is cemented and cleaned outside it | Possible; undetected cement increases as the margin goes deeper |
| Typical technical problems | Screw loosening; more ceramic chipping | Loss of retention: 4.1% of cemented crowns at five years |
| Typical biological problems | Fewer fistulas, less suppuration | Higher rate of fistula formation and suppuration |
| Esthetics and occlusion | Access hole must exit lingually or occlusally; angled channels help | No access hole; intact occlusal surface |
| Implant position | Needs prosthetically driven placement | More forgiving |
Neither lasts longer. A review of 73 studies prepared for the 2013 consensus conference of the International Team for Implantology (ITI) found five-year survival of 96.03% for cemented and 95.55% for screw-retained reconstructions (P = .69), with no difference when single crowns or fixed partial dentures were analyzed separately. An earlier review reported 96.5% for cemented and 89.3% for screw-retained single crowns, but the screw-retained estimate was imprecise (95% CI 64.9% to 97.1%) and the difference was not significant.
The ITI consensus states that "a universal recommendation cannot be made for either cementation or screw retention." The choice comes down to the case in front of you.

Choose a Screw-Retained Crown When...
- The access exits through the central fossa or the cingulum. A posterior single crown, often zirconia on a Ti-base, or an anterior crown with cingulum access: retrievable, with no cement in the mouth and no esthetic cost.
- The implant is deep and the margin would sit well below the mucosa. Undetected cement rises with margin depth; a screwmentable crown is the other option here.
- The patient has a history of periodontitis. Cement remnants are linked to peri-implantitis.
- The case is a multi-unit bridge or a full arch. One review found a trend to fewer complications with screw retention, and repair is easier.
The condition: screw retention needs prosthetically driven implant placement. Two findings explain why several reviews prefer it: excess cement and easy retrieval.
Excess cement is the main biological risk
In Wilson's endoscopic study, excess cement was found at 34 of 42 implants with peri-implant disease and at none of 20 healthy controls. In a clinical study of 53 cemented crowns, undetected cement increased the deeper the margin sat. A 2017 systematic review called excess cement a possible risk indicator and recommended margins at the level of the mucosa, with early follow-up.
of implants with peri-implant disease in an endoscopic study had excess cement. After it was removed, 74% showed no signs of disease (Wilson, 2009).
Not every study finds a difference: a meta-analysis of six randomized trials found similar rates of mucositis and peri-implantitis, and a 2025 AO/AAP review found no significant difference in bone loss. But in a 7.5-year randomized trial of zirconia-based crowns in the esthetic zone, cemented crowns had twice the bleeding on probing (40% vs. 20%) and more total complications (84.2% vs. 38.1%). Cement causes trouble when left behind, and a 2022 review recommends screw retention to limit excess cement.
A loose screw is the easier problem to fix
Screw loosening is the most frequent technical problem with implant single crowns, at 8.8% over five years, although newer screw designs have cut it by almost half. For single crowns, Sailer et al. estimated five-year technical complications of 24.4% with screw retention and 11.9% with cement; pooled across all reconstruction types, the ITI review found more with cement. Screw-retained crowns also show more ceramic chipping.
What tips most reviewers is retrieval: problems with a screw-retained crown are easier to treat because it comes off easily, and Sailer et al. judged screw retention preferable for that reason.
Choose a Cement-Retained Crown When...
The ITI consensus lists cement as an option for short spans with margins at or above tissue level, for esthetics when the screw access is transocclusal or the implant malpositioned, for an intact occlusal surface and for lower initial cost, and warns that cementation needs great caution. In practice, cement is a sound choice when:
- Straight access would exit facially, beyond what an angled channel corrects. Cement the crown on a custom abutment; implant consensus guidelines list poor access as a reason to cement.
- An intact occlusal surface matters. A cemented crown has no access hole in it.
- The span is short and the margins sit at or above the mucosa. That matches the consensus guidelines.
- The implant position is less than ideal. Cement is more forgiving of position.
Cement costs nothing in survival. The typical technical problem is loss of retention, second only to screw loosening among implant single crowns, in 4.1% of cemented crowns at five years. The typical biological problem is a higher rate of fistula formation and suppuration. So keep the margin at or above the mucosa where possible, and say on the Rx where you want it.
Edge Cases: Screwmentable Crowns, Facial Access and Hidden Cement
Three situations do not fit either list neatly.
Screwmentable crowns
A screwmentable (hybrid) crown is cemented to a titanium base (Ti-base) outside the mouth, and the one-piece unit is screwed in. A systematic review concluded that screwmentable prostheses combine passive fit, retrievability and control of excess cement, but of its 24 studies only one was a randomized trial and 14 were in vitro. For Ti-base hybrid single crowns, a meta-analysis found 100% one-year survival and under 1% complications, and called for five-year trials. It suits screw-retained zirconia or lithium disilicate crowns, especially with deep margins. For a full guide, see Screwmentable Implant Crowns: Cemented to a Ti-Base, Retrieved Like a Screw-Retained Crown.

Anterior crowns where the access would come out facially
A straight screw channel exits wherever the implant points. In the anterior maxilla, where buccal bone is often thin or missing, that can mean a labial access hole: the classic reason to cement.
How far one widely used titanium-base system lets an angled screw channel move the access hole off the implant axis (Atieh et al., 2025).
A 2025 meta-analysis of 167 nonmolar single crowns found angled-channel crowns matched cemented ones for bone levels and pink esthetic scores, with less bleeding on probing; screw loosening and porcelain fracture were slightly, not significantly, more frequent. So an angled channel often keeps an anterior crown screw-retained. Beyond the system's range, cement onto a custom abutment, with the margin at or above the mucosa where possible.
Finding excess cement on radiographs
Radiographs are a poor check for leftover cement. In the same study of 53 cemented implant crowns, remnants were visible radiographically in only 4 cases mesially and 6 distally (Linkevicius et al., 2013). Resin cements are harder still: mostly translucent and not radiopaque (Sailer et al., 2022). A clean radiograph does not prove a clean margin, so the protection has to come first: a shallow margin and an early check.
What the Lab Needs on the Rx
If any of these are missing, we have to call before design can start:
- Implant system: manufacturer and line, per site.
- Platform and diameter: per tooth.
- Scan body: brand and type, to match the correct library file; for analog cases, the impression coping.
- Abutment: Ti-base, custom titanium or zirconia, stock, or multi-unit. If you supply the Ti-base, its brand and height.
- Retention: screw-retained, screwmentable or cemented; for cemented crowns, where you want the margin.
- Screw channel: straight only, or angled allowed, with the maximum angle you accept.
- Material and shade: see our zirconia vs. e.max comparison.
- Soft tissue: if a provisional shaped the emergence profile, scan it.

Ordering Implant Crowns From Us
- Implant restorations: see our implant options.
- Warranty: up to 20 years on screw-retained implant abutments and up to 7 years on final restorations. Policies and warranties.
- Made in house: every case, with no outsourcing, in our 7,000 sq. ft. facility at 2308 McDonald Ave, Brooklyn, NY, by more than 35 technicians. Founded in 2007 by Gary Fingerman.
- Scan review: digital scans are reviewed before production. Submit a digital case.
- Turnaround: from 5 business days on most restorative cases, while implant crowns and custom abutments take longer; rush is decided case by case. Send a case or call 877-335-5221.
Related Guides
- Why Implant Screws Loosen, and How to Prevent It
- Implant Abutments Explained: Stock vs. Custom vs. Ti-Base vs. Multi-Unit
- How to Scan Implants: Scan Bodies, Common Mistakes and What to Send the Lab
FAQ
Are screw-retained implant crowns better than cemented ones?
Not for survival: about 96% at five years for both. Screw retention wins on retrievability and cement control; cement wins when the access hole would compromise esthetics or occlusion.
Do screw-retained crowns loosen more often?
For single crowns, some reviews report more technical events with screw retention (24.4% vs. 11.9% over five years), but a loose screw is easy to reach and retighten.
Does excess cement really cause peri-implantitis?
It is a risk indicator: in observational studies, 33% to 100% of peri-implant disease at cemented implants was associated with excess cement. Randomized trials found similar rates with both methods, so keep margins shallow and check early.
Can a cement-retained implant crown be removed?
Yes, but not by simply unscrewing it: with no access hole over the abutment screw, retrieval takes more work, and the crown may have to be cut off. For a cemented zirconia crown, see How to Remove a Zirconia Crown: Burs, Sectioning Time and Protecting the Tooth.
What torque should I use on the screw?
The implant manufacturer's value, not the lab's: torque values differ between systems, platforms and screws, and angled-channel screws also need their own driver. Follow the manufacturer's current instructions for the exact screw we send.
Sources (14)
- Wittneben JG, et al. Clinical performance of screw- versus cement-retained fixed implant-supported reconstructions: a systematic review. Int J Oral Maxillofac Implants. 2014;29 Suppl:84-98. doi:10.11607/jomi.2014suppl.g2.1
- ITI Academy Consensus Database. Clinical Performance of Screw- versus Cement-Retained Implant-Supported Fixed Reconstructions (5th ITI Consensus Conference, 2013). academy.iti.org
- Sailer I, et al. Cemented and screw-retained implant reconstructions: a systematic review of the survival and complication rates. Clin Oral Implants Res. 2012;23 Suppl 6:163-201. doi:10.1111/j.1600-0501.2012.02538.x
- Wilson TG. The positive relationship between excess cement and peri-implant disease: a prospective clinical endoscopic study. J Periodontol. 2009;80(9):1388-1392. doi:10.1902/jop.2009.090115
- Linkevicius T, et al. The influence of the cementation margin position on the amount of undetected cement. Clin Oral Implants Res. 2013;24(1):71-76. doi:10.1111/j.1600-0501.2012.02453.x
- Staubli N, et al. Excess cement and the risk of peri-implant disease: a systematic review. Clin Oral Implants Res. 2017;28(10):1278-1290. doi:10.1111/clr.12954
- Reis INRD, et al. Incidence of peri-implant disease associated with cement- and screw-retained implant-supported prostheses: a systematic review and meta-analysis. J Prosthet Dent. 2025;134(1):100-108. doi:10.1016/j.prosdent.2023.08.030
- Lin GH, et al. The influence of prosthetic designs on peri-implant bone loss: an AO/AAP systematic review and meta-analysis. J Periodontol. 2025;96(6):634-651. doi:10.1002/JPER.24-0144
- Kraus RD, et al. A 7.5-year randomized controlled clinical study comparing cemented and screw-retained one-piece zirconia-based implant-supported single crowns. Clin Oral Implants Res. 2024;35(12):1669-1675. doi:10.1111/clr.14346
- Sailer I, et al. Prosthetic failures in dental implant therapy. Periodontol 2000. 2022;88(1):130-144. doi:10.1111/prd.12416
- Atieh MA, et al. Angled screw channel-retained vs. cement-retained implant crowns in nonmolar sites: a systematic review and meta-analysis. J Esthet Restor Dent. 2025;37(7):1706-1720. doi:10.1111/jerd.13463
- Sarafidou K, et al. Screwmentable implant-supported prostheses: a systematic review. J Prosthet Dent. 2023;130(1):35-47. doi:10.1016/j.prosdent.2021.08.027
- Zhang M, et al. Clinical performance of implant-supported single hybrid abutment crown restoration: a systematic review and meta-analysis. J Prosthodont Res. 2024;68(1):63-77. doi:10.2186/jpr.JPR_D_22_00279
- Linkevicius T, et al. Does residual cement around implant-supported restorations cause peri-implant disease? A retrospective case analysis. Clin Oral Implants Res. 2013;24(11):1179-1184. doi:10.1111/j.1600-0501.2012.02570.x
Reviewed by Gary Fingerman, founder and CEO of Elegant Dental Laboratory, Brooklyn, New York (founded 2007). Last reviewed: September 28, 2026.